

Signs your antidepressant isn’t working can be difficult to assess on your own. Little change after a full trial, improvement that stalled partway, symptoms returning after months of feeling better, or side effects that outweigh the benefit are all reasons to arrange a medication review rather than make a change yourself.
Keep taking what you have been prescribed while you arrange that conversation. At MindVita, a psychiatric provider can review what you are taking, how long you have been on it, and what has and has not changed since you started, before discussing what to do next. You can book an appointment when you are ready.
How Long Do Antidepressants Take to Work?
Often longer than people expect, which is why one of the first questions at a review is how long you’ve been taking the medication. A few weeks without noticeable change doesn’t mean a medication has failed, and the earliest signs of improvement aren’t always the ones people watch for.
The National Institute of Mental Health [1] states that antidepressants usually take four to eight weeks to work and that problems with sleep, appetite, energy, and concentration often improve before mood lifts. It also notes that it may take several tries to find the medication that works best for a particular person.
That point is worth emphasizing. Needing a second or third medication is a recognized part of treating depression rather than an indication that nothing will help, and it is more common than many people realize while they are going through it.
Signs Your Antidepressant Isn’t Working
No single experience confirms this, and none of the patterns below amounts to a diagnosis on its own. Each is a reason to arrange a review rather than wait another month, especially if it has continued well past when you expected to notice a change in how you feel day to day.
A study funded by the National Institute of Mental Health [2], known as STAR*D, found that about one third of participants reached remission on the first medication they were given, with roughly another 10 to 15 percent improving without reaching remission. The study then examined what helped those who did not.
The patterns below are among the most common reasons people arrange a review.
Nothing Has Shifted After a Full Trial
Several weeks at a steady dose with no change in sleep, energy, appetite, or mood is worth raising. Your prescriber can judge whether the trial has genuinely been long enough.
Improvement Stalled Partway
You felt better for a while, then plateaued well short of feeling like yourself. A partial response is common and one of the clearest reasons a prescriber revisits the plan.
Symptoms Came Back After Months of Feeling Better
Many people searching for what to do when antidepressants stop working are describing this. When symptoms return on a medication that previously helped, it’s a recognized pattern worth reviewing promptly.
Side Effects Outweigh the Benefit
A medication that improves your mood but leaves you unable to sleep or function at work is not meeting the goal of treatment. This is worth raising plainly.
Daily Life Has Not Followed Your Mood
Questionnaire scores can improve while work, relationships, and motivation remain affected. How you are functioning day to day matters as much as how you rate your mood.
Specific details help at the appointment. When each change started, what the dose has been, which weeks were more difficult, and what you have already tried will shape the conversation more usefully than a general sense that the antidepressant is not working.
Possible Reasons Symptoms Remain
An antidepressant not working can have several explanations, and not all of them are about the drug itself. Time and dose are the usual first checks at any review. After that, a prescriber generally considers whether something else is contributing before concluding the medication needs changing.
One possibility deserves particular attention. The National Institute of Mental Health [3] explains that when signs of bipolar disorder are missed and a depressive episode is treated with an antidepressant alone, a manic episode or rapid cycling may be triggered, which is why antidepressants are not used by themselves in bipolar disorder.
Other contributors a prescriber may ask about include:
- Doses missed often enough to affect the medication’s level
- Thyroid problems, sleep disorders, chronic pain, or other medical conditions
- Alcohol or other substances
- Interactions with other prescriptions or supplements
- Ongoing stress, grief, or circumstances that medication alone will not resolve
- A diagnosis that may need revisiting as more history emerges
If you want detail on a specific medication rather than the general picture, MindVita has separate articles on Pristiq and Zoloft that cover those drugs individually.
Why Not to Stop or Change Your Medication on Your Own
Stopping suddenly can create a second problem alongside the first one. Lowering a dose, skipping days, or stopping altogether without speaking to your prescriber may bring on withdrawal effects, increase the risk of symptoms returning, and make it considerably harder to determine what was actually happening in the first place.
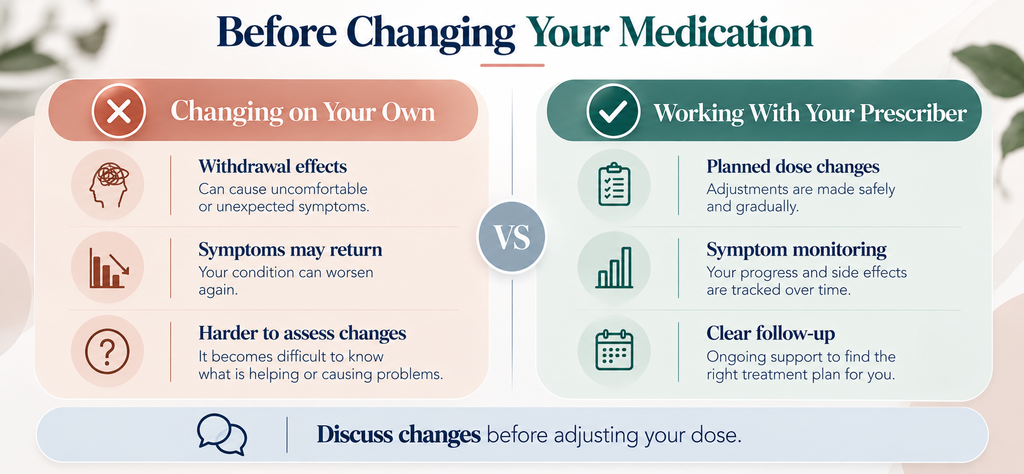
NAMI [4] describes antidepressant discontinuation syndrome as an example of what can follow stopping a medication too quickly, with uncomfortable symptoms usually appearing within a few days and sometimes taking a few weeks to settle. It advises working with a provider to plan a slight decrease instead.
There is a practical reason beyond comfort. Withdrawal effects and returning depression can feel similar, and distinguishing between them is much easier when a prescriber knows exactly what changed and when. If cost, side effects, or uncertainty are making you consider stopping, those are all appropriate things to raise at a review.
Options a Prescriber May Consider
There are several options, and the right one depends on your history, how long you have been treated, what has helped, and what you can tolerate. Adjusting the dose, switching medications, adding a second one, bringing in or changing therapy, and re-examining the diagnosis are all on the table.
The STAR*D findings reported by the National Institute of Mental Health [2] give some sense of what the next step offered. Among participants whose first medication did not work, about 25 percent became symptom-free after switching to a different one, and about one third became symptom-free after adding a second medication to the first.
These are study averages across a large group, not a prediction for any individual, and the researchers noted that the odds narrowed with each additional step. The practical point remains that a first medication that does not work is a starting point, not a final answer. Medication management is largely this process of reviewing and adjusting treatment over time.
When to Book a Review or Seek Urgent Care
Book a review when a pattern above has persisted, when side effects affect your daily life, or when you start wondering whether to stop. You do not need to wait for a scheduled follow-up, and you do not need to have made up your mind about what should change.
Some situations need faster attention. NIMH [1] advises that people taking antidepressants be watched closely, especially during the first few weeks of treatment and when a dose is changed, since children, teenagers, and young adults under 25 may experience an increase in suicidal thoughts or behavior during those periods.
If you are having thoughts of suicide or self-harm, the 988 Suicide and Crisis Lifeline [5] offers free, confidential support 24 hours a day, seven days a week by call, text, or online chat. Call 911 if you or someone else is in immediate danger. A scheduled appointment is not the appropriate route for an emergency.
Book a Medication Review With MindVita
Maybe you have been telling yourself to give it another month since spring. Maybe you raised it once, were advised to continue, and have not brought it up again. Or you are taking a medication you are no longer sure is helping, without a clear plan for what happens next.
At MindVita, we start by reviewing what you have already tried, including the doses, timelines, and what worked before it stopped. If what you actually need is a different prescriber rather than a different prescription, MindVita’s guide to switching psychiatric providers covers how to transfer care without a gap in your medication. You can book an appointment online and bring the details with you.

FAQs
Should I keep taking my medication while I wait for the appointment?
Yes, unless your prescriber has advised otherwise. Stopping in the days before a review removes information your provider needs and may add withdrawal effects to the symptoms you already have. If something urgent develops while you wait, contact the practice rather than adjusting the dose yourself or waiting for the scheduled appointment.
How do I tell the difference between the medication not working and a hard few weeks?
This can be difficult to judge on your own, which is why the overall timeline matters more than any single week. How long it has lasted, whether it followed a specific event, and whether sleep and appetite changed alongside your mood all help a prescriber distinguish between them. Recording dates as they occur is more reliable than recalling them later.
Does needing to switch mean I have treatment-resistant depression?
Not by itself. That term has a specific clinical meaning involving adequate trials of more than one medication, and a single medication that did not suit you does not meet it. Your prescriber can explain where your history sits and what that does or does not change about your options.
Will my prescriber think I am being difficult if I say it is not working?
A good prescriber will want to know, since treatment that isn’t helping isn’t worth continuing by default. Being specific about what has and has not changed is more useful than softening the message. If you raise concerns repeatedly and nothing changes, that is useful information about the fit with that provider.
Can therapy help if medication alone has not?
It may. Therapy and medication work differently, and some people respond better to both than to either one alone. Whether that applies to you depends on your symptoms, history, and preferences, which is worth raising at the same review rather than as a separate decision.
References
- National Institute of Mental Health (NIMH). “Mental Health Medications.” https://www.nimh.nih.gov/health/topics/mental-health-medications
- National Institute of Mental Health (NIMH). “Sequenced Treatment Alternatives to Relieve Depression (STAR*D): All Medication Levels.” https://www.nimh.nih.gov/funding/clinical-research/practical/stard/allmedicationlevels
- National Institute of Mental Health (NIMH). “Bipolar Disorder.” https://www.nimh.nih.gov/health/publications/bipolar-disorder
- National Alliance on Mental Illness (NAMI). “Stopping Medications.” https://www.nami.org/treatments-and-approaches/mental-health-medications/stopping-medications/
- 988 Suicide and Crisis Lifeline. https://988lifeline.org/



